
Recallab › Question bank › Medicine › Electrolyte › #50057
SIADH
A 66-year-old smoker with a newly found lung mass is admitted confused. Serum sodium is 116 mEq/L. He is clinically euvolaemic, with no oedema, normal blood pressure, normal jugular venous pressure and normal skin turgor. Thyroid and adrenal function are normal and he is on no diuretic. Which set of results would confirm the likely diagnosis?
- correctA. Serum osmolality 245, urine osmolality 480, urine sodium 55 mEq/L
- B. Serum osmolality 245, urine osmolality 70, urine sodium 55 mEq/L
- C. Serum osmolality 245, urine osmolality 480, urine sodium 8 mEq/L
- D. Serum osmolality 300, urine osmolality 480, urine sodium 55 mEq/L
Explanation
Key fact
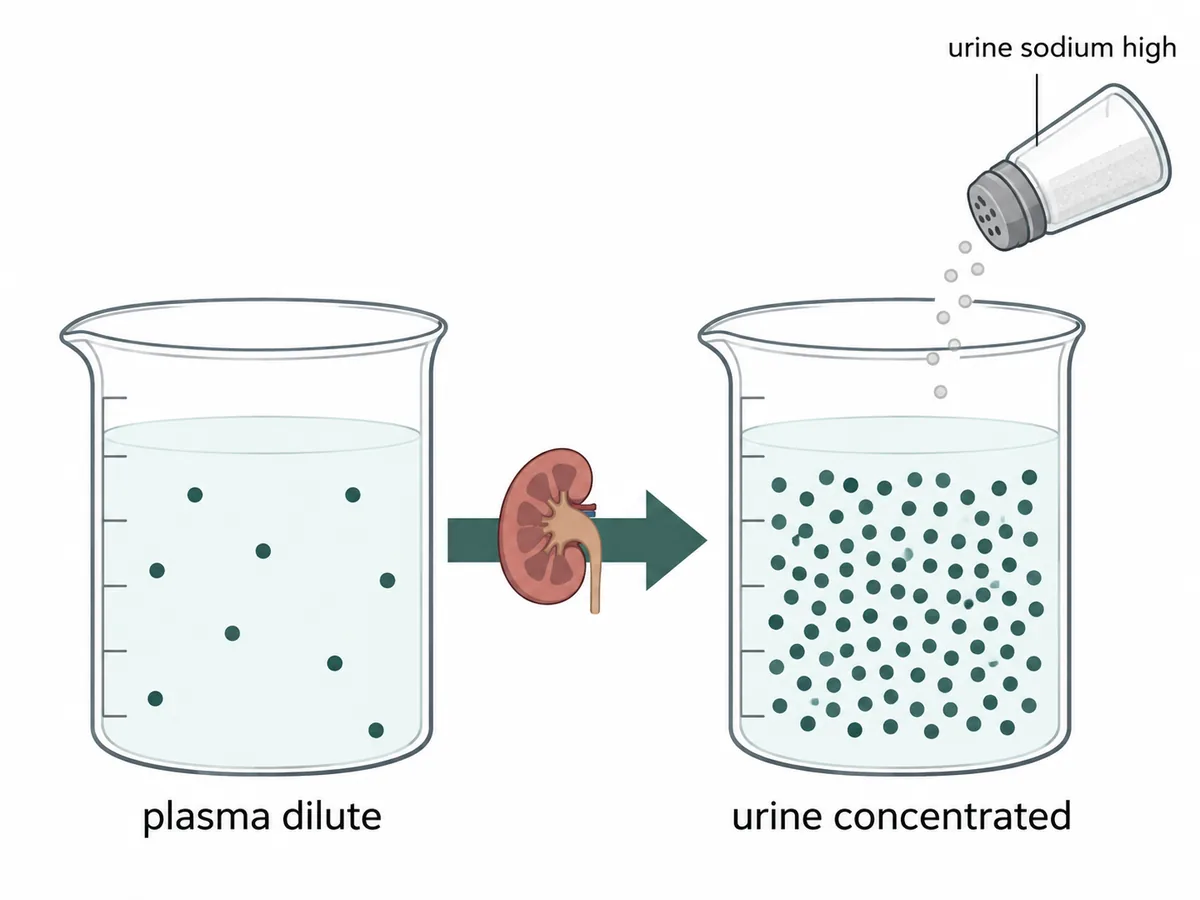
In SIADH the urine is inappropriately concentrated and the urine sodium is high, while the blood is dilute.
Serum osmolality 245, urine osmolality 480, urine sodium 55. Dilute blood with concentrated urine, and no sodium conservation, is SIADH.
How it happens
- Confirm the hyponatraemia is real: serum osmolality is low at 245.
- Assess volume: he is euvolaemic, which narrows it to SIADH or endocrine causes.
- Thyroid and adrenal function are normal, so those are excluded.
- Now ask whether the kidney is diluting. Urine osmolality of 480 says it is not.
- That is inappropriate antidiuresis given a serum osmolality of 245.
- Urine sodium above 40 shows the kidney is not volume-depleted.
Dilute blood, concentrated urine
Why not the others
- B. Serum osmolality 245, urine osmolality 70, urine sodium 55 — shows a maximally dilute urine, which is the appropriate response. That is primary polydipsia.
- C. Serum osmolality 245, urine osmolality 480, urine sodium 8 — shows the kidney conserving sodium hard, which means true volume depletion - vomiting, diarrhoea or third spacing.
- D. Serum osmolality 300, urine osmolality 480, urine sodium 55 — is not hypotonic at all. A normal or high osmolality with low sodium means pseudohyponatraemia or hyperglycaemia.
Remember
Dilute blood, concentrated urine, plenty of urinary sodium. All three together, and nothing else fits.
Go deeper
Small cell lung carcinoma is the classic tumour cause; others are central nervous system disease, pneumonia, and drugs such as carbamazepine and SSRIs.
Correct no faster than 8 mEq/L in 24 hours. Overcorrection causes osmotic demyelination, and it is irreversible.
Hypertonic saline is for seizures or coma only; otherwise fluid restriction, with tolvaptan or urea if that fails.
Harrison's Principles of Internal Medicine, 22nd ed. (McGraw Hill, 2025).